
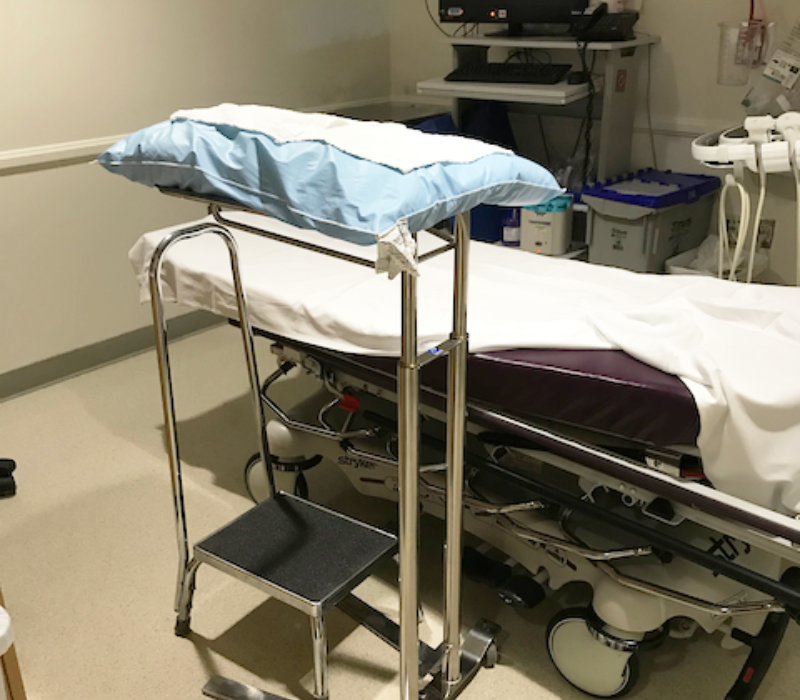
In an imaging procedure room, a patient with a large pleural effusion sits on the edge of the bed, short of breath and visibly anxious. In front of the patient is a rolling overbed table topped with a stack of pillows, and the patient leans over it. The table drifts slightly on its casters. The pillows compress and slide. A nurse plants one hand on the table and the other on the patient’s shoulder to hold everything in place, leaning in at an awkward angle. The ultrasound technician marks the entry site, and the pulmonologist prepares the needle. Everyone in the room is hoping no one moves.
Thoracentesis positioning is a patient handling task. An improvised overbed table and pillow setup is neither stable nor an engineering control. It leaves the patient, the target site, and the caregiver exposed to avoidable risk. Improper positioning compromises patient safety, prolongs procedures, and reduces clinical efficiency. Safe Patient Handling and Mobility (SPHM) research confirms that engineering controls are the preferred solution because they create permanent change that eliminates risk at the source.
This final article in the series explains four things:
- Why thoracentesis depends on a precise, stable posture
- Why the improvised setup fails patients and staff
- How the SPH Medical Epidural Positioning Device (EPD) works as an engineering control in imaging
- What the EPD delivers for clinicians, patients, and your facility
Why Thoracentesis Requires a Precise, Stable, Forward Leaning Posture
Thoracentesis drains excess fluid from the pleural space. Its safety depends on a patient who sits upright, leans forward, and holds that posture without shifting from site marking through drainage.
A pleural effusion is fluid that collects between the lungs and the chest wall. It leaves patients breathless and uncomfortable. To drain it, a clinician inserts a needle or catheter between the ribs. That clinician is often a pulmonologist, and the procedure is frequently guided by ultrasound.
Posture matters for two reasons:
- Leaning forward widens the intercostal spaces. This gives the clinician clearer, safer access to the pleural space.
- Stillness keeps the target valid. The ultrasound marked entry point is accurate only if the patient stays in the exact posture used during marking.
Reaching that posture is difficult for these patients, and holding it is harder still. Shortness of breath, anxiety, fatigue, weakness, and body habitus all work against them.
Unstable positioning puts several priorities at risk:
- Accuracy of the ultrasound marked entry site
- Patient safety during needle and catheter placement
- Procedure length and imaging room throughput
- Caregiver strain from bracing the patient or the setup
Stable positioning is not a comfort feature for thoracentesis. It is a core safety requirement. Yet the tool most imaging departments rely on was never designed to deliver it.
Why the Overbed Table and Pillow Stack Is Not an Engineering Control
The overbed table and pillow stack is an improvised workaround, not an engineering control. Because it is unstable, the job of holding the patient still falls to the patient and to the staff in the room.
The Hierarchy of Controls
SPHM programs rely on a clear principle. Engineering controls change the equipment or environment to remove a hazard at its source. Work practices depend on people compensating correctly every single time.
A rolling table and loose pillows remove nothing. They demand constant human correction, and the setup fails in predictable ways:
- Drifting casters: An overbed table rolls under a patient’s weight, so the surface the patient leans on is never truly fixed.
- Sliding pillows: Pillows compress unevenly and slip, which prevents a consistent posture.
- Invalidated markings: Every shift in posture moves the entry site. The ultrasound marking is no longer accurate, and risk during needle placement rises.
- A hidden caregiver hazard: Nurses and techs end up steadying the table or bracing the patient. They hold sustained static loads while leaning and reaching in the flexed postures that research links to musculoskeletal injury.
The Evidence Is Clear
Manual bracing carries the same risks as any other manual patient handling task, and the numbers are sobering:
- Hospital workers sustained 46,000 work related back injuries in 2001.
- Back injuries account for 33 percent of workers’ compensation costs.
- The cumulative weight a nurse handles in one typical shift equals roughly 1.8 tons.
OHSU Biodynamics laboratory testing confirms that manual patient handling generates far higher physical loads than using assistive devices. In addition, thirty five years of research show that body mechanics training alone does not reduce caregiver injury. Better technique cannot make an unstable setup safe.
Here is how the two approaches compare:
- Overbed table and pillows: drifts and slides, varies from room to room, requires staff to steady it by hand, and invalidates site marking when the patient shifts
- Engineered positioning with the EPD: stays put, remains consistent for every patient, removes the need for manual bracing, and keeps the marked site valid through drainage
Consider a common scenario. An ultrasound technician marks the ideal entry point, then watches the pillows slump and the patient slide sideways. The team must reposition, scan, and mark again while a nurse braces the patient by hand.
An improvised setup that requires people to hold it steady is a hazard, not a solution.
How the SPH Medical EPD Works as a Purpose Built Engineering Control
The SPH Medical Epidural Positioning Device is also known as the Epidural Chair. It provides a stable, padded support that holds patients in the ideal forward leaning posture and stays put through needle and catheter placement.
- Stable surface: The EPD does not drift or slide, so the patient rests securely instead of balancing on a moving table.
- Consistent posture: Every patient is supported the same way. The intercostal spaces stay open, and the target site stays still.
- Valid markings: The posture used for ultrasound marking is the posture maintained through drainage.
- No manual bracing: Staff move from steadying the patient and the table to monitoring and reassuring the patient.
- Proven versatility: The same device supports epidurals in labor and delivery, spinal blocks in the OR, and thoracentesis in imaging. One standardized solution serves several departments.
What Changes in the Imaging Procedure Room
- The patient leans onto a fixed, supportive surface instead of a rolling table.
- The nurse shifts from bracing to observing.
- The ultrasound marking stays accurate from preparation through placement.
- Positioning becomes a written protocol step rather than an improvised setup.
Patient handling equipment is among the SPHM interventions with the strongest evidence for reducing caregiver injury. When an imaging department retires the pillow stack and writes the EPD into its thoracentesis protocol, every patient receives the same stable, standardized setup.
Benefits for Ultrasound Technicians and Pulmonologists
A motionless, consistently positioned patient keeps the ultrasound marking valid. It also gives the pulmonologist stable, reliable access to the pleural space.
- Markings stay accurate: Ultrasound technicians mark the entry site once, and it remains accurate through placement.
- Faster imaging: A still patient means fewer repeat scans and less time chasing a moving target.
- Stable access: Pulmonologists work with open intercostal spaces and a steady target from start to finish.
- First attempt success: Less patient movement supports first attempt placement and lowers complication risk.
Picture a pulmonologist completing several procedures in one session. In every case, the patient is positioned the same stable way, and there are no stops to reposition a slipping patient.
When the equipment holds the patient still, both clinicians can concentrate fully on precision and safety.
Patient Comfort and Satisfaction
Patients who feel securely supported can breathe, stay calm, and hold still. That makes the procedure safer and far less distressing.
Balancing on a rolling table while short of breath, with a needle near the chest, is genuinely frightening. The EPD takes over the work of holding the patient steady, which makes the experience less intimidating and more comfortable. Clinicians have reported noticeable improvements in patient comfort and procedural efficiency with the device.
Patients benefit from:
- Greater comfort and stability throughout the procedure
- Reduced anxiety and a stronger sense of security
- Lower risk of complications tied to sudden movement
- Higher patient satisfaction scores
A supported patient is a steady patient, and a steady patient is a safer one.
Facility ROI: Safer Procedures, Faster Throughput, Healthier Staff
The EPD delivers returns across patient safety, imaging efficiency, and workforce protection:
- Workers’ compensation savings: The average cost of a single back injury was $13,445. Eliminating manual bracing reduces strain injuries and the claims that follow.
- Workforce retention: Roughly 12 percent of nursing personnel consider leaving their jobs each year because of injury. Protecting staff protects experience.
- Fewer repeat scans: When markings stay accurate, the team avoids repeat imaging and the delays that come with it.
- Faster throughput: A consistent, reproducible setup shortens preparation time and keeps imaging rooms moving.
- Ratings and accreditation: A visible commitment to standardized safety supports facility ratings and potential accreditation.
To demonstrate results, track these measures before and after adoption:
- Patient satisfaction scores
- Complication rates
- Setup and procedure times
- Staff injury reports
The EPD is not a comfort accessory. It is a high return investment that supports performance and process improvement goals.
No One in the Room Should Have to Hope the Patient Stays Still
Thoracentesis depends on a precise, stable, forward leaning posture. The overbed table and pillow stack cannot deliver that posture, and it shifts the burden of stability onto patients and staff. The SPH Medical EPD keeps the patient still, keeps the marking valid, and removes manual bracing. It does so in alignment with ANA and AORN SPHM standards.
This principle runs through the entire series. Whether the procedure is an epidural in labor and delivery, a spinal block in the preoperative area, or a thoracentesis in imaging, the solution is the same. Replace manual support and improvised setups with one standardized engineering control.
Start by observing how thoracentesis is positioned in your imaging department. Identify where staff are steadying tables or patients by hand, and bring your findings to your SPHM or value analysis committee.
Contact SPH Medical today for more information or to schedule a demonstration of the EPD.